Well, that's not *exactly* true; we got to know the NG tube *quite* well, actually. But it's gone, and as the saying goes, "na na na na, na na na na, heeeeyyy, good bye!"
We had our regular Cranialfacial clinic today and the surgical nurse looked at Ethan's G-Tube/surgical site and said it looked really good and we could start using it (we were told originally Wednesday was the first day we could use it). So we did - right then and there (as he was due for a feeding at that time).
It was actually quite appropriate that Ethan himself had yanked out the NG tube just before we left for Children's. We decided to not put it back in just in case we got the go ahead to start using the G-Tube, and, well, there you go.
The clinical visit was very encouraging. His primary cranialfacial pediatrician was very nonchalant about everything - Ethan is progressing so well that he is not concerned about *anything*.
They had originally talked about bringing the surgical schedule in substantially (macrostomia repair in March, mandibular repair within the next 2 years) but since Ethan is doing so well and since his oral feedings improved so much recently, they felt the need to do this has now abated and we stick to our original surgical plan (macrostomia repair in May-ish and mandibular repair many years off). Normally, I would be very disappointed that the surgeries are being delayed, but in this instance, the reason behind delaying them is that everything is going so well. And in Ethan's case, the later, the better - as this gives him more time to grow and develop.
The mandibular repair is now pushed out to probably around 7 years of age. Another additional reason they were originally thinking to do the first surgery at 3-5 years (and then was subsequently brought in to 1-3 years) was to address his breathing/respiratory issues. But Ethan is improving here too - enough to the point that they do not want to do/risk such an invasive surgery so early. (The original thought was that if they lengthen the jaw, this would help open up his airway more by pushing the tongue and all related structures farther out). In addition, there is the very slight possibility (in Ethan's case, the doctors said it was highly unlikely but the possibility still exists (i.e. it is a non-zero probability event)) that there may be no jaw surgeries until he is 18 years old. They will simply continue to monitor him and see how his jaw affects his eating/breathing/speech and continually evaluate/re-evaluate. Like the doctors, I do not hold out a lot of hope for having no surgeries until age 18. Most likely, it will be around age 7. This also means that the CT scan scheduled for when he is knocked out during the macrostomia repair has been cancelled (which is good - less exposure to radiation over his lifetime).
Another upshot of this is that the G-tube may come out earlier now. We thought that it may stay for 2-3 years but with the jaw surgery now pushed out several years, they said they would not leave the G-tube in that long. The criteria for taking it out is Ethan must be 100% orally fed for 2 months with good growth trajectory during those 2 months and absolutely nothing going in the G-tube. If we can get there, and it is post-macrostomia repair, it is entirely possible we could lose the G-tube within a year. If we happen to get to the 2 month criteria *before* the macrostomia repair, they want to leave it in just in case his oral feedings fall off post-surgery.
They also commented that Ethan seems to be a little ahead of the curve in terms of his cognitive and motor development. The doctors were very impressed that he can already basically sit by himself (if only for a few moments) and that he is so alert and attentive. (Recall from (much) earlier posts that Cranialfacial Microsomia brings with it a 10%-15% chance of cognitive impairment). So this was very encouraging to hear.
So to sum up, as of 1/25/10, this is where we stand:
Ethan is doing very well in his growth and development. Next major surgery to excise the ear tags, fix the macrostomia, and clip his frenulum is back to around the May time frame. Next major surgery after that to address the epibulbar dermoid still remains around the September time frame. He is off the NG tube and strictly on the G-tube. If all goes well and he continues to make progress in oral feeding, we could lose the G-tube within a year. Their appraisal is that Ethan is doing so well, our next regular clinical visit won't be for another 2-3 months.
The general prognosis, in the doctor's own words: "Ethan is in the clear now". There was originally concern for his growth trajectory (since he was such a poor oral feeder) as well as his respiratory issues. But he seems to have gotten over the hump (like achieving the necessary activation energy, to borrow an analogy from chemistry) and things are going very well now. As they put it, moving forward, there should be very few (if any) surprises and any issues that follow will be expected (he may need his tonsils and adenoids removed by the time he is a toddler, he will probably need braces, etc).
The only other thing to note: the doctor noted that Ethan's dermoid seemed to be thicker. Ophthalmology mentioned that the dermoid should not change it's characteristics in any way moving forward. We expect to hear back to see if ophthalmology wants to evaluate this. If they do, regardless of what they find (if anything) we do *not* anticipate this will change the surgery date to remove the dermoid.
In all, it was a *very* good day and we are 3 for 3 for good news. Now if only the markets would deliver such good news on a reliable basis... (for those of you who might be interested at all, yours truly is scared enough of those idiots in Washington and what they may or may not do (i.e. actually *not* reappoint Bernake) that I purchased March 100 SPY puts as protection - yes I'm that worried...).
- bob
Showing posts with label Goldenhars. Show all posts
Showing posts with label Goldenhars. Show all posts
Monday, January 25, 2010

Tuesday, December 15, 2009
If Bad News Occurred In An Uninhabited Forest, Could It Get Worse?
If no news is good news, what I wouldn't give to have no news for a change.
So we got back from our visit at Children's with Ophthamology and ENT. The Reader's Digest version: Ethan has severe astigmatism in his right eye due to the presence of the dermoid. Starting from around 2-3 years of age, he will need glasses and patching to correct this and prevent the onset of amblyopia (a word you do *not* want to hear). The good news is that his eyes and vision are otherwise fine. His left eye is perfectly fine. The right eye, apart from the astigmatism is fine. The ophthamologist says that the dermoid is unlikely to change moving forward and whatever damage it was going to do: it's already done. His opinion is that while this is not good news by any stretch of the imagination, it is 'typical' for children such as Ethan suffering from Cranialfacial Microsomia: it is typical for children with CFM to have dermoids of this size, it is typical for dermoids of this size to cause astigmatism, and it is typical for the astigmatism to be of this severity.
There is no need to take any corrective action until about 2-3 years as his vision is still developing and that any difficiency in visual acuity from the astigmatism is outweighed (and will be until about 2-3 years of age) by the normal difficiency in visual accuity that is due to his age (i.e. his vision won't be developed enough until age 2-3 for the astigmatism to be noticed). As a side note: if no corrective action were to be taken at all, amblyopia wouldn't set in until probably around age 5 or so, so it is not of any immediate concern (hence no action until age 2-3).
Ophthamology also believes that in light of the above, the dermoid removal is purely optional and cosmetic (if we left it in, it wouldn't make the astigmatism worse or cause any other problems, and if we remove it, it won't make the astigmatism go away). However, if we wish to have it excised, he recommends postponing it until at *least* one year of age if not later as the surgery is extremely difficult before one year of age. Moreover, it is currently impossible to judge the depth of the dermoid and as such, impossible to know how it will look after surgery: they cannot *completely* excise it - what they do is shave off the top. So this leaves some of the dermoid behind which means that there will still be some opacity in the region of where the dermoid currently resides. How opaque it will be depends on how much is left behind which depends on how thick the dermoid is (which they won't know until pre-op which is at least 8 months away currently). Regardless, he did say it would "look much better".
ENT didn't reveal much. There is some inflamation of the tissues above the vocal chords. This may be due to reflux, it may be due to the presence of the NG tube, or it may be due to a combination of both. This result is pretty much congruent with what we expected after coming out of last week's visit and recommendation of the ph probe. I suppose the good news here is that they didn't see anything out of the ordinary or abnormal.
We discussed the possibility of having his frenulum clipped to allow for more tongue movement (this has been OTPT's recommendation all along) and they (ENT) recommend to do it while under general anesthesia during his upcoming macrostomia repair (they felt that there might be some bleeding and hence couple of stitches may be required and hence it wouldn't be something to be done in clinic). They also recommended moving his (more comprehensive) hearing test up from 8 months or so to within the next 1-2 months.
We are still awaiting scheduling of the ph probe. We hope to have word on this within the next 24-48 hours. With the holidays upcoming, we expect it won't be scheduled until January.
We also have an upcoming (regular) appointment with CranialFacial in January.
-bob
Thursday, December 10, 2009
There Are No Straight Lines In Nature
They say there are no straight lines in nature. Pan's corollary: More so with Ethan.
We got back from Children's just now. This appointment was to assess the viability of the g-tube and true to form, it's not that simple with Ethan. While everything with his esophagus, stomach and basically his whole upper G-I checks out, it is unknown if Ethan *actually* has acid reflux. He has always been put on medications for it because it was assumed that he had it to some degree and he always seemed to do a little better while on the medication: but he has never actually been formally diagnosed with acid reflux. This has now become very important. G-tubes, once inserted, can cause acid reflux or aggravate an existing acid reflux condition. Since the whole point of inserting the g-tube is to make things generally better for him, if it will aggravate an existing acid reflux condition, then the simple g-tube insertion is no longer an option.
Ethan will undergo a 24 hour test (a ph probe) to monitor his esophagus and conclusively determine if he is indeed suffering from acid reflux and if so, to what degree. His appointment with ENT this coming Monday won't be conclusive or definitive enough. This test has yet to be scheduled (probably within the next two weeks) and will require an overnight stay in Children's. Results from the test should be forthcoming within the 24 hours following. From there, they can decide what they will do. If he has no acid reflux or it is not significant, they will go ahead with the simple g-tube insertion.
If the acid reflux is significant, then it gets quite a bit more complicated. There are a few options, none of which we find particularly attractive. The primary option is to then undergo a laparoscopic Nissen fundoplication (http://en.wikipedia.org/wiki/Nissen_fundoplication). The basic point of this is to create a one way valve to allow food to pass through to the stomach but prevent the acid from coming back up the esophagus. Then the g-tube can be inserted. However, side effects from this (there are many, actually: see the article) are that the stomach may initially not be able to empty as well as before and gas cannot travel back up the esophagus (so he can't burp anymore). So this means that the feeding patterns may need to change and he may need to be burped through his g-tube. The Nissen surgery is meant to be permanent. However, the stitches used in the procedure may come loose with time and if so, the acid reflux returns. Another option is to leave the ng-tube (what he has now) but thread it past the stomach directly into the small intestine. However, this is obviously something that can only be done at Children's and if we do this, and if Ethan should happen to pull out the tube, we *cannot* reinsert it - it means another trip to Children's to reinsert the tube. While this is an "option", I doubt it will be considered a viable option - since the whole point of the g-tube was to eliminate the ng-tube in the first place.
We were told that we should hear by Monday about when the ph probe will be scheduled for.
It just keeps going on and on... :-(
-bob
Throughout this whole journey with Ethan I have felt sad or stressed at times, but have really tried to find the positive in everything...something to be thankful for or something that has gone positively whether it be that Children's Hospital treats Ethan's condition and we don't have to fly anywhere, a successful feeding or passing a test. Any progress at all. Today was the first time (even with him being in the NICU at Evergreen, all the medically related appointments, or being admitted to Children's) that I felt frustrated and depressed...just generally down. I know Ethan's got the best docs, physical therapists, and nurses and i'm thankful that they are so thorough and take such good care of him...I guess i'm just frustrated that nothing has been as straight forward as I would like it to be. There always seems to be a few detours to get to the end of what we thought was a straight road and there are a lot of roads to travel still! I need to remind myself that God never gives you more than you can handle. Whenever Ethan looks at me with that little crooked smile, my heart melts and that reminds me that all this work is worth it! I also need to be thankful that Jonathan is healthy and is such an easy kid. He has put up with all of this and is such a good big brother!
-Dina
A Glimmer Of Hope

As of 12/01/09:
We just got back from another routine visit to Children's.
They are *very* pleased with his growth/weight gain. Overall, they are very pleased with him - how he looks, reacts/responds, his head control, his alertness - everything.
They will schedule some tests in a few weeks to determine what kind of g-tube to insert and which surgical procedure they will use. The tests are to confirm there are no problems with his stomach, or any surprises of any other type. He is also scheduled to go into Children's on 12/15 to see Othamalogy and ENT - mostly because those teams have not yet seen him. He will most likely get his g-tube inserted in Jan. They feel they could probably get it done before Christmas, but with us going up to Vancouver for Christmas (unless we somehow don't get Ethan's passport in time), I didn't want to go up and be away from Children's and have some unwanted surprises occur with it. While the g-tube is temporary, in Ethan's case, temporary means 1-3 years. Even if his oral feedings improve to where he can be fed 100% orally, they feel they will leave the g-tube in for a while since he will be undergoing surgeries that may interfere with his feeding (like the surgical repair to his mouth) so the g-tube gives them options to keep his feedings on track.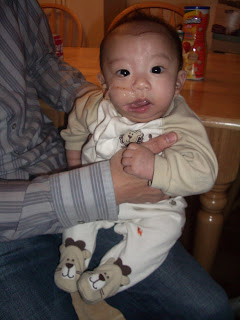
The surgery to repair his macrostomia will most likely be brought in to about March now. The doctors feel his oral feedings will not improve significantly until the macrostomia is repaired and they would like to bring that in by a couple of months if possible (as his doctor put it: "as soon as possible"). We meet with the plastic surgeon again in January and at that time he can give us better visibility as to the viablity of bringing in the surgical schedule - but after today's visit, the way they were talking - it seemed almost certain it will happen in March now. They would also like to bring in the surgical schedule for his mandible repair (if possible) - also because he feels that this would help his oral feeding significantly. So now instead of occuring at around 4-5 years of age, it might be anywhere between 1-3 years. Again, the plastic surgeon will need to assess this. What the current (very early plan) is that while he is out (sedated) for the macrostomia repair, they will also do a CT scan of his jaw so they can get a better understanding of what needs to be done and proceed down the right path. As the plastic surgeon put it today - there are several paths this could go so it all depends on what is there to work with and what is there developmentally. This is also probably why his doctor wants to leave the g-tube in for a prolonged duration - if the mandible repair occurs at, say 2 years, best to have the g-tube in there to feed him while he recovers from the surgery.
Most likely, if we do indeed procede with the macrostomia repair in March, the ear tags will probably be excised at the same time.
No word on the dermoid as that is up to Othamology which we won't see until 12/15/09.
They do not know why his breathing has gotten worse in the last few weeks. They suspect it may be related to the reflux (the acid may cause more mucus build up resulting in the raspy breathing). ENT (on 12/15/09) will probably be able to give more insight/visibility on this.
We just got back from another routine visit to Children's.
They are *very* pleased with his growth/weight gain. Overall, they are very pleased with him - how he looks, reacts/responds, his head control, his alertness - everything.
They will schedule some tests in a few weeks to determine what kind of g-tube to insert and which surgical procedure they will use. The tests are to confirm there are no problems with his stomach, or any surprises of any other type. He is also scheduled to go into Children's on 12/15 to see Othamalogy and ENT - mostly because those teams have not yet seen him. He will most likely get his g-tube inserted in Jan. They feel they could probably get it done before Christmas, but with us going up to Vancouver for Christmas (unless we somehow don't get Ethan's passport in time), I didn't want to go up and be away from Children's and have some unwanted surprises occur with it. While the g-tube is temporary, in Ethan's case, temporary means 1-3 years. Even if his oral feedings improve to where he can be fed 100% orally, they feel they will leave the g-tube in for a while since he will be undergoing surgeries that may interfere with his feeding (like the surgical repair to his mouth) so the g-tube gives them options to keep his feedings on track.

The surgery to repair his macrostomia will most likely be brought in to about March now. The doctors feel his oral feedings will not improve significantly until the macrostomia is repaired and they would like to bring that in by a couple of months if possible (as his doctor put it: "as soon as possible"). We meet with the plastic surgeon again in January and at that time he can give us better visibility as to the viablity of bringing in the surgical schedule - but after today's visit, the way they were talking - it seemed almost certain it will happen in March now. They would also like to bring in the surgical schedule for his mandible repair (if possible) - also because he feels that this would help his oral feeding significantly. So now instead of occuring at around 4-5 years of age, it might be anywhere between 1-3 years. Again, the plastic surgeon will need to assess this. What the current (very early plan) is that while he is out (sedated) for the macrostomia repair, they will also do a CT scan of his jaw so they can get a better understanding of what needs to be done and proceed down the right path. As the plastic surgeon put it today - there are several paths this could go so it all depends on what is there to work with and what is there developmentally. This is also probably why his doctor wants to leave the g-tube in for a prolonged duration - if the mandible repair occurs at, say 2 years, best to have the g-tube in there to feed him while he recovers from the surgery.
Most likely, if we do indeed procede with the macrostomia repair in March, the ear tags will probably be excised at the same time.
No word on the dermoid as that is up to Othamology which we won't see until 12/15/09.
They do not know why his breathing has gotten worse in the last few weeks. They suspect it may be related to the reflux (the acid may cause more mucus build up resulting in the raspy breathing). ENT (on 12/15/09) will probably be able to give more insight/visibility on this.
-bob
Back To Square One...
 As of 9/11/09:
We had thought that we were done with the NG tube as Ethan managed to put down a whole bottle several times (albiet - it was tough slogging). However, for breathing issues, we brought Ethan in to Children's and what started as a routine visit became a 48 hour stay. And the NG tube was here to stay...
---------------------------------------------------------------------
(Again, gleaned from status emails)
Ethan has always been (from birth) a noisy breather. However, in the last week, it has gotten much worse. We finally called it in and we were advised to bring him to Children's to have them look at it. Since it occurred the most during feedings, they wanted OTPT (occupational/physical therapy) to look at him in regards to his feeding/swallowing. After that initial look, they decided to have cranialfacial have a look as they didn't think it had anything to do with his swallowing but more of an airway blockage. After examining him some more, they recommended admitting him to Children's for observation. (So what began as a 1-2 hour visit turned into a 9 hour visit for me, and a 48 hour visit for Dina).
After 48 hours, and trying various things, they discharged him. They changed his sleeping arrangements/positioning as well as made more amendments to his feeding plan.

Ethan now sleeps on a modified wedge/sling (I can't remember the exact name of this thing). He sleeps face down on the wedge (head up towards the top) in a sling attached to the wedge to prevent him from sliding/rolling down the wedge and to help keep him prone (face down).
Last week was also the first week that Ethan failed to gain any weight. The doctors at Children's speculate that he does have an airway obstruction - his tongue. When laying on his back, it seems to obstruct his breathing. This accounts not only for the (very) noisy sleeping but in his difficulty in eating. They speculate that he expends so much energy trying to breath (especially during feeding) that all his caloric intake goes towards trying to breathe and eat.

Hence, we have changed his sleeping position to a prone one allowing him to breathe with much more ease (he is at times almost silent now - he has *never* been silent). Eating is slightly different. If a feeding is going well, it is capped at 30 minutes and the rest (if any is left) is tube fed. If a feeding is going very poorly, it is simply aborted and we will tube feed him for that feeding. His caloric intake per feeding was also bumped up. He is also on antacids for reflux. Contrary to our hopes, the feeding tube will remain for quite some time now.
The goal is to make breathing and eating easier for him so that he can put on weight and hopefully simply outgrow his airway problem. Since he will not be capable of significant movement until 3-4 months (that's when infants normally start to be able to roll over) we buy a few months of time to allow for significant weight gain and for him to gain strength. When he does start to move more (i.e. 3-4 months from now), the air way problem may go away, or may resurface, or something else may happen. The doctors cannot say what will happen. All that is known at this point is that these fixes seem to work and will at least buy more time before anything else needs to be done (if at all).
-bob
Tuesday, December 1, 2009
The Story So Far...
Gleaned from various status emails:
------------------------------------

8/28/09
It's been a long(!) two weeks but Ethan is home now. We gave Jonathan his presents from Ethan (a new Thomas train and a box of cookies). Jonathan loves his new train. Could care less about having Ethan home. :-) But at least we got a "Thank you, Ethan" out of him. Currently scheduled to be back at Children's on Sept. 21.
8/27/09
As of 8/27/09: We are still on track to come home today. The call on whether to come home today or tomorrow is entirely ours. The hospital is satsified with discharging him at any time now. If we feel we need an extra day to work with the feeding equipment and get familiar with it, we can stay. If we feel OK with it, we can leave. The equipment showed up yesterday. I used it yesterday and Dina used it last night. Not very hard at all (after you've used it once, it almost seems obvious how to use it). The opthamologist showed up yesterday to examine his epibulbar dermoid. While large, her opinion is that it is not currently interfering with his vision. She currently sees no indication to think his vision is impaired in any way. It will, however, need to be continually monitored and, ultimately, most likely will have to be removed. They ran the hearing test again today. They have to run the test when the baby is sleeping and not moving. Ethan apparently was very restless in his sleep resulting in them having to run the test 3 times (movement can give false positives). He passed 2 out of 3 times. I personally view this with some suspicion and will hold judgment until his hearing is evaluated at Children's. But it does give some hope that he may not actually require surgery in his middle ear. We contacted Children's and they are supposed to get back to us today regarding his next appointment. I hope this will be within the next 1-2 weeks. His feeding is showing improvement but it is painfully slow. But progress is progress. The goal is to get him off the feeding tube entirely within 1-2 months. Ethan failed his car seat test. This means we need to buy a new car seat even though we already have one (he's too small for it currently). We will buy a new one and use it for all of 1-2 months and put him in the old one (that fits in the stoller) when he's bigger.
8/22/09
We got back to the hospital from Children's about 4:30PM. Several specialists examined him. It is now officially Cranialfacial Microsomia as the diagnosis. The doctor doesn't like the other names (Goldenhar's Syndrome, Hemifacial) - but that's his personal preference. The diagnosis is the same which is what we first diagnosed. Nothing will be done to Ethan surgically until he is about 1 year old. At that point, they will probably address the lateral cleft in his mouth, and the ear tags (at our request - the ear tags are purely cosmetic and Children's leaves that entirely up to the family). The reason for the wait has to do with the proxmity of these areas to the facial nerve. Ethan's jaw is actually far worse than I thought. His entire lower left jaw is underdeveloped/malformed. On his left side (good side), the Ramus is smaller than it should be (the bone that extends from the base of the Mandible to the upper jaw where it hinges together). His right Ramus is almost non-existant. Moreover, the base of the mandible on the right side is shorter. This can and will be addressed surgically, but not until he is about 2-3 years of age. It is almost certain he will be deficient in hearing on his right side. To what extent is not currently known, but like the article you sent me, it won't be addressed until he is at least 4 years of age. The epibulbar dermoid on his right eye the doctor felt will probably need to be removed due to it's size. This again will not take place until he is at least 1 year old. His spine cannot be properly evaluated until around one year of age. The plan going forward is once we get discharged from the hospital, we will setup another appointment with Children's in the following 1-2 weeks (depending on when we can get an appointment). At that time, they will concentrate on working with us to get him feeding better. The other disciplines will also come to examine him as a sort of "heads up" as for what will be coming their way in the next year. After that appointment, they will tell us when is the next time we should come in. They will monitor him over the next few months. If anything changes, the surgical schedule may be brought in (i.e. the epibulbar dermoid is growing faster than they would like/anticipate - so it will be removed sooner than after 1 year, etc). But if nothing changes for the worse, we are probably on track for having the first procedure done around 1 year from now. The doctors at Children's felt that Ethan can be discharged now and sent home with the feeding tube. We will work with Children's to work on his feeding to get him off the tube. This will be a long and time consuming process. They have shown us methods to tape that side of his mouth shut (basically closing off the mouth where it normally should be closed) and it seemed to help with the feedings but he is still having difficulty. The hospital has begun the process of discharge. With luck, he will be home within a week. They need to setup an initial plan for us going forward for working on his feeding, ordering the equipment for us (for the feeding tube) or point us to a vendor, clearing everything through insurance, etc. So in a nutshell: Ethan will be home in a week (give or take). He will still be on a feeding tube but will will be working with Children's to get him off that. This will take some time. We will have "regular" appointments with Children's for monitoring and evaluation. He will require at minimum of 7 surgeries (3 for the jaw - minimum, 1 for the mouth, 1 for the ears, 1 for the ear tags, and 1 for the eye). Surgeries will begin at around 1 year of age and continue until probably around 4-5 years of age. The studies on this indicate that it is genetic. They do not understand the genetics. Ours is a typical case - no history of it on either side and then it appears sporatically. Therefore, they think the genetics behind it are quite complicated - some specific set of genes on one side with specific set of genes on the other side coming together in a sort of "perfect storm". Therefore, currently, they believe the odds of siblings having children with CFM are very low - i.e. because it appeared in our family now, the odds are still low that Elaine, Andy, or Ryan will have this problem.
 8/19/09
The on call NICU physician said he had indeed seen this before (this was a different doctor). His diagnosis is specifically Goldenhar's Syndrome - which is basically what we suspected: it's a type of Hemifacial Microsomia. He is sure of it. From his examinations, it seems that Ethan is very healthy and that most of the manifestations of the syndrome are cosmetic. Ethan had his hearing test done. The left ear passed. The right ear did not. So they will retest again tomorrow. If the results are the same, we will go to Children's to have a much more comprehensive hearing test done. If he fails the test tomorrow, it does not necessarily mean he does not have hearing in the right ear. It means we need a more comprehensive test. He thinks the dermoids in his right eye should not impair his vision. They may lead to astigmatism later on in life but he said the team at Children's will evaluate and decide if they need to be removed. If they do not impair sight and will not cause any future problems, then the only issue is one of cosmetics and we can have them optionally removed at a later date. His recommendation was to start the process of meeting with Children's immediately as it is in fact a "process" you go through - you don't just call for an appointment. We start the process now because it may be months before we actually get into to Children's to meet with their team. However, he did say that if through some miracle they had an opening and could see us before Ethan is even discharged, the hospital will find a way to make sure we do not miss the open slot at Children's - even if that means they need to send a nurse with us to Children's. In other words, the hospital will do what it can to help us through the process and will in no way be a hinderance to us if Children's is ready before Ethan is. Dina has already made the initial call to Children's and we are waiting to hear back from them. Ethan is not making huge progress in eating. He is hungry more often and they are feeding him increasingly larger amounts and he is keeping it all down. The issue is that he still is not very capable of feeding himself (either by breast or bottle). However, when I did go to visit this afternoon, he sucked down 42 ml orally leaving only 8 ml for the feeding tube. But it seems he's not always consistent.
8/17/09
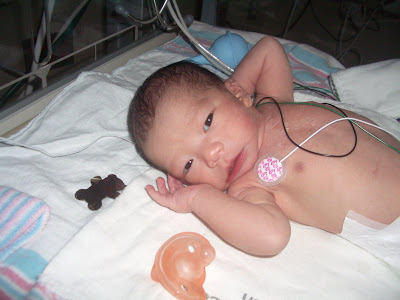
So as of 8/17/09, this is where we are: Ethan was born with Hemifacial Microsomia. It is sometimes referred to as Goldenhar Syndrome or Cranialfacial Microsomia (among the dozen names this condition has). There is no official diagnosis yet as only the staff at Children's is qualified to make this diagnosis. I spent countless hours researching his irregular physiology until I came to this conclusion. The hospital staff seems to concur with my conclusion - but again - only Children's can confirm my/our suspicions. He has trouble feeding and consequently is in NICU where they are working to get him to feed regularly/properly. Some progress has been made but he will not be discharged from the hospital/NICU until he can consistently breastfeed/bottlefeed 30ml per session. He is not able to do this so they are supplementing his breast/bottle feedings with a feeding tube. The reason is that he tires easily and usually falls asleep before he can ingest that amount orally. This *may* be due to the fact that he was 2 weeks early. This probably has nothing to do with his HFM (though it *may* contribute as he may have to work harder to feed than normal because of his mouth). Once he is discharged and can come home, we will be then set up to meet with the cranialfacial team at Children's for a proper clinical diagnosis and then a course of (surgical) treatment. The good news (it's increasingly hard to come by recently) is that Children's specializes in this and are extremely familiar with this. Assuming this is indeed what it is (and I have never been more sure of anything in my life). Ethan is otherwise very healthy. Cranial and renal ultrasounds revealed nothing nor did the echo cardiogram and the abdominal x-rays. Hearing tests have not yet been run but anecdotal behavior suggests his hearing is OK (that is our opinion - nothing official). He is not in any discomfort, all his internal organs are all functioning, and he is behaving fine. Dina was discharged from the hospital on Sunday. She is staying at the hospital in Ethan's room so she can provide regular (every 3 hours) breastfeedings. I am now at home with Jonathan. My folks have left (will return after Labour Day - they could not stay longer as they need to take specific medications and did not bring enough to prolong their stay). Dina's mom will be helping me at home so I can resume working from home (or back on site if required/requested).
 8/14/09
So to keep you updated or to inform you if I inadvertantly did not initially inform you (apologies if so): Dina gave birth by c-section this morning at 12:39AM. Dina's doing really well (especially compared to last time). Ethan (currently his name - may change again!) was born 5 lbs 8 oz. I forgot his length. He does have a few issues and is currently in NICU. He was taken to NICU after birth, spent the night with us in Dina's room, but after the AM pediatric assessment, was sent back to the NICU. He's had some tests and the current status from the doctor is that he has not heard anything and that no news is good news (i.e. if something were wrong, they would have informed him immediately). Dina is slated to be discharged Sunday (tentative). No ETA on Ethan being discharged from NICU. One issue is that he is not eating and is currently being tube fed. Even if there are no other issues, they will not let him out until he is eating.
------------------------------------

8/28/09

It's been a long(!) two weeks but Ethan is home now. We gave Jonathan his presents from Ethan (a new Thomas train and a box of cookies). Jonathan loves his new train. Could care less about having Ethan home. :-) But at least we got a "Thank you, Ethan" out of him. Currently scheduled to be back at Children's on Sept. 21.
8/27/09
As of 8/27/09: We are still on track to come home today. The call on whether to come home today or tomorrow is entirely ours. The hospital is satsified with discharging him at any time now. If we feel we need an extra day to work with the feeding equipment and get familiar with it, we can stay. If we feel OK with it, we can leave. The equipment showed up yesterday. I used it yesterday and Dina used it last night. Not very hard at all (after you've used it once, it almost seems obvious how to use it). The opthamologist showed up yesterday to examine his epibulbar dermoid. While large, her opinion is that it is not currently interfering with his vision. She currently sees no indication to think his vision is impaired in any way. It will, however, need to be continually monitored and, ultimately, most likely will have to be removed. They ran the hearing test again today. They have to run the test when the baby is sleeping and not moving. Ethan apparently was very restless in his sleep resulting in them having to run the test 3 times (movement can give false positives). He passed 2 out of 3 times. I personally view this with some suspicion and will hold judgment until his hearing is evaluated at Children's. But it does give some hope that he may not actually require surgery in his middle ear. We contacted Children's and they are supposed to get back to us today regarding his next appointment. I hope this will be within the next 1-2 weeks. His feeding is showing improvement but it is painfully slow. But progress is progress. The goal is to get him off the feeding tube entirely within 1-2 months. Ethan failed his car seat test. This means we need to buy a new car seat even though we already have one (he's too small for it currently). We will buy a new one and use it for all of 1-2 months and put him in the old one (that fits in the stoller) when he's bigger.
8/22/09

We got back to the hospital from Children's about 4:30PM. Several specialists examined him. It is now officially Cranialfacial Microsomia as the diagnosis. The doctor doesn't like the other names (Goldenhar's Syndrome, Hemifacial) - but that's his personal preference. The diagnosis is the same which is what we first diagnosed. Nothing will be done to Ethan surgically until he is about 1 year old. At that point, they will probably address the lateral cleft in his mouth, and the ear tags (at our request - the ear tags are purely cosmetic and Children's leaves that entirely up to the family). The reason for the wait has to do with the proxmity of these areas to the facial nerve. Ethan's jaw is actually far worse than I thought. His entire lower left jaw is underdeveloped/malformed. On his left side (good side), the Ramus is smaller than it should be (the bone that extends from the base of the Mandible to the upper jaw where it hinges together). His right Ramus is almost non-existant. Moreover, the base of the mandible on the right side is shorter. This can and will be addressed surgically, but not until he is about 2-3 years of age. It is almost certain he will be deficient in hearing on his right side. To what extent is not currently known, but like the article you sent me, it won't be addressed until he is at least 4 years of age. The epibulbar dermoid on his right eye the doctor felt will probably need to be removed due to it's size. This again will not take place until he is at least 1 year old. His spine cannot be properly evaluated until around one year of age. The plan going forward is once we get discharged from the hospital, we will setup another appointment with Children's in the following 1-2 weeks (depending on when we can get an appointment). At that time, they will concentrate on working with us to get him feeding better. The other disciplines will also come to examine him as a sort of "heads up" as for what will be coming their way in the next year. After that appointment, they will tell us when is the next time we should come in. They will monitor him over the next few months. If anything changes, the surgical schedule may be brought in (i.e. the epibulbar dermoid is growing faster than they would like/anticipate - so it will be removed sooner than after 1 year, etc). But if nothing changes for the worse, we are probably on track for having the first procedure done around 1 year from now. The doctors at Children's felt that Ethan can be discharged now and sent home with the feeding tube. We will work with Children's to work on his feeding to get him off the tube. This will be a long and time consuming process. They have shown us methods to tape that side of his mouth shut (basically closing off the mouth where it normally should be closed) and it seemed to help with the feedings but he is still having difficulty. The hospital has begun the process of discharge. With luck, he will be home within a week. They need to setup an initial plan for us going forward for working on his feeding, ordering the equipment for us (for the feeding tube) or point us to a vendor, clearing everything through insurance, etc. So in a nutshell: Ethan will be home in a week (give or take). He will still be on a feeding tube but will will be working with Children's to get him off that. This will take some time. We will have "regular" appointments with Children's for monitoring and evaluation. He will require at minimum of 7 surgeries (3 for the jaw - minimum, 1 for the mouth, 1 for the ears, 1 for the ear tags, and 1 for the eye). Surgeries will begin at around 1 year of age and continue until probably around 4-5 years of age. The studies on this indicate that it is genetic. They do not understand the genetics. Ours is a typical case - no history of it on either side and then it appears sporatically. Therefore, they think the genetics behind it are quite complicated - some specific set of genes on one side with specific set of genes on the other side coming together in a sort of "perfect storm". Therefore, currently, they believe the odds of siblings having children with CFM are very low - i.e. because it appeared in our family now, the odds are still low that Elaine, Andy, or Ryan will have this problem.
 8/19/09
The on call NICU physician said he had indeed seen this before (this was a different doctor). His diagnosis is specifically Goldenhar's Syndrome - which is basically what we suspected: it's a type of Hemifacial Microsomia. He is sure of it. From his examinations, it seems that Ethan is very healthy and that most of the manifestations of the syndrome are cosmetic. Ethan had his hearing test done. The left ear passed. The right ear did not. So they will retest again tomorrow. If the results are the same, we will go to Children's to have a much more comprehensive hearing test done. If he fails the test tomorrow, it does not necessarily mean he does not have hearing in the right ear. It means we need a more comprehensive test. He thinks the dermoids in his right eye should not impair his vision. They may lead to astigmatism later on in life but he said the team at Children's will evaluate and decide if they need to be removed. If they do not impair sight and will not cause any future problems, then the only issue is one of cosmetics and we can have them optionally removed at a later date. His recommendation was to start the process of meeting with Children's immediately as it is in fact a "process" you go through - you don't just call for an appointment. We start the process now because it may be months before we actually get into to Children's to meet with their team. However, he did say that if through some miracle they had an opening and could see us before Ethan is even discharged, the hospital will find a way to make sure we do not miss the open slot at Children's - even if that means they need to send a nurse with us to Children's. In other words, the hospital will do what it can to help us through the process and will in no way be a hinderance to us if Children's is ready before Ethan is. Dina has already made the initial call to Children's and we are waiting to hear back from them. Ethan is not making huge progress in eating. He is hungry more often and they are feeding him increasingly larger amounts and he is keeping it all down. The issue is that he still is not very capable of feeding himself (either by breast or bottle). However, when I did go to visit this afternoon, he sucked down 42 ml orally leaving only 8 ml for the feeding tube. But it seems he's not always consistent.
8/17/09
So as of 8/17/09, this is where we are: Ethan was born with Hemifacial Microsomia. It is sometimes referred to as Goldenhar Syndrome or Cranialfacial Microsomia (among the dozen names this condition has). There is no official diagnosis yet as only the staff at Children's is qualified to make this diagnosis. I spent countless hours researching his irregular physiology until I came to this conclusion. The hospital staff seems to concur with my conclusion - but again - only Children's can confirm my/our suspicions. He has trouble feeding and consequently is in NICU where they are working to get him to feed regularly/properly. Some progress has been made but he will not be discharged from the hospital/NICU until he can consistently breastfeed/bottlefeed 30ml per session. He is not able to do this so they are supplementing his breast/bottle feedings with a feeding tube. The reason is that he tires easily and usually falls asleep before he can ingest that amount orally. This *may* be due to the fact that he was 2 weeks early. This probably has nothing to do with his HFM (though it *may* contribute as he may have to work harder to feed than normal because of his mouth). Once he is discharged and can come home, we will be then set up to meet with the cranialfacial team at Children's for a proper clinical diagnosis and then a course of (surgical) treatment. The good news (it's increasingly hard to come by recently) is that Children's specializes in this and are extremely familiar with this. Assuming this is indeed what it is (and I have never been more sure of anything in my life). Ethan is otherwise very healthy. Cranial and renal ultrasounds revealed nothing nor did the echo cardiogram and the abdominal x-rays. Hearing tests have not yet been run but anecdotal behavior suggests his hearing is OK (that is our opinion - nothing official). He is not in any discomfort, all his internal organs are all functioning, and he is behaving fine. Dina was discharged from the hospital on Sunday. She is staying at the hospital in Ethan's room so she can provide regular (every 3 hours) breastfeedings. I am now at home with Jonathan. My folks have left (will return after Labour Day - they could not stay longer as they need to take specific medications and did not bring enough to prolong their stay). Dina's mom will be helping me at home so I can resume working from home (or back on site if required/requested).
 8/14/09
So to keep you updated or to inform you if I inadvertantly did not initially inform you (apologies if so): Dina gave birth by c-section this morning at 12:39AM. Dina's doing really well (especially compared to last time). Ethan (currently his name - may change again!) was born 5 lbs 8 oz. I forgot his length. He does have a few issues and is currently in NICU. He was taken to NICU after birth, spent the night with us in Dina's room, but after the AM pediatric assessment, was sent back to the NICU. He's had some tests and the current status from the doctor is that he has not heard anything and that no news is good news (i.e. if something were wrong, they would have informed him immediately). Dina is slated to be discharged Sunday (tentative). No ETA on Ethan being discharged from NICU. One issue is that he is not eating and is currently being tube fed. Even if there are no other issues, they will not let him out until he is eating.
-bob
Subscribe to:
Posts (Atom)