Showing posts with label hearing. Show all posts

Tuesday, May 7, 2013

Update on Ethan

Ethan  had more regularly scheduled followups at Children's  on 5/6/13.  

Everything was pretty much the same and they're happy with how he's doing.  He's still on track for major jaw surgery at about age 7-9.  However, we got more details of what this will eventually involve.  Once this starts - it will not be a good year for Ethan...  :-(  

Most likely there will be one major jaw surgery before the main one to lengthen his jaw.  This will involve taking bone and cartilage grafts from his ribs and using it to create more bone and/or joints at the joint where his jaw hinges together.  It is not known definitively if this surgery will be required until they take a CAT scan to see what they have to work with - and they will not do this until about age 7 when he's getting into the window of time where they want to do the procedure.  However, it was the doctor's opinion that he would be very surprised if Ethan did not require this surgery.  After this surgery, it will be at least 6 months (minimum) before the jaw distraction surgery can take place.  

After this surgery, the jaw distraction (jaw lengthening) can take place.  This will involve breaking the jaw in two places - one on each side - and inserting the distraction device.  Once in place, there will be one month of actually using the device (turning the screw on each device on a nightly basis to lengthen it and hence induce bone to grow in the gap).  There will be at least two visits per week to Children's during this time to monitor the bone growth.  X-rays will probably be taken at each visit.  This period could go longer than one month but the doctor estimates that amount of bone that needs to be created will take around 1 month.  After this process, the device is left in the jaw for about another 2 months.  At this point - the device is what is holding his jaw together so it is left in place while the jaw heals over the next 2 months.  

At the end of the healing period, there is the final surgery to remove the devices.  After the devices are removed, he should be healed enough that no further healing is required - essentially the day after the devices are removed he is free to eat anything and do any and all activities.  However, for the 3+ months prior (i.e. when the devices are in place) he will be on a severely restricted regimen - very soft foods only, probably very little physical activities, etc.  

It will probably be a very unpleasant year for Ethan...  :-(  They did say they will accommodate you if you want a summer time surgery so he doesn't have to go to school with the devices implanted (most parents opt for this so summer is a busy time for them in terms of this type of surgery) but given that the entire process will be a minimum of 3 months - that will be his whole summer vacation so I'm sure he will be *very* unhappy about that.  

Since it's at least 4 years away, I probably will choose to simply not think about it until then.  We do not meet w/ the plastic surgeon again for another followup for another 2+ years at this point.  So nothing will change in terms of the surgical schedule so no need to think about it.  So I'm choosing not to.  

Other news: Ethan had another regular hearing screen and the results came back the same as last time so this is good.  Essentially, his hearing is not expected to change, but as he gets older, they can get more reliable data from him and that is the reason for the periodic hearing screens.  So far, the data is fairly stable: he is giving pretty consistent data telling us what we already know.  

His otolaryngologist saw him and there was nothing new there either.  There was some talk of possibly inserting ear tubes to help drain fluid from his right ear to possibly improve the slight hearing loss he has - but given it will require general anesthesia and every time Ethan requires a general he also needs to be intubated, we all agreed to simply leave it as an option on the table and do nothing for now.  

He meets with this ophthalmologist at Children's in two weeks.  We expect to walk out of there with glasses for Ethan.  We hope to be surprised and come out w/ nothing - but we're really not counting on it.  
 
 
- bob

Tuesday, January 24, 2012

Mixed Results With A Bias To The Upside

Ethan had a plethora of regularly scheduled followups at Children's yesterday. The bottom line coming out of all the appointments is that Ethan is doing well; nothing to see here - move along, move along!

He was evaluated by a speech pathologist/therapist and the recommendation was that Ethan continue with speech therapy. He has made tremendous progress since he began, but there is still work to be done (he still does a lot of consonant substitution) and he is probably not ready yet to be discharged from his therapists' services.

Ethan also met with his plastic surgeon. His post-surgical scars are coming along very nicely. It was felt that he is on track for his next major surgery (the jaw distraction) at about age 8 (but see note below). There is the outside possibility that he may not have it until age 18, but that seems pretty improbable. Basically, the road map is as follows: if, as he grows, the mandibular hypoplasia is really not that bad at all when he reaches age 8, then they will postpone any further surgical intervention until age 18 when the jaw is almost fully grown and they can at that time not only do the jaw distraction, but all the orthodontic work that may need to be done to correct any jaw/teeth misalignment. If he needs the surgery at age 8, there will be a followup surgery to do the final corrections at age 18. Between ages 8-ish and 18, they prefer to do nothing if it at all possible. So age 8-ish is crucial as it is really a fork in the road. So while it is possible that he may not need the surgery at age 8, it seems unlikely as his mandibular hypoplasia would have to be quite minimal. But there is always hope... He will have a followup with his plastic surgeon in about one year.

We also went over the results of his sleep study. While the results are hugely improved over the results of his pre-op sleep study, on their own, they are not great results. Before his tonsillectomy and adenoidectomy, he had up to 24 sleep apnea occurrences per hour peaking with up to 48 per hour during REM sleep. Post surgery, this fell down to about 6-8 per hour. This is a vast improvement. However, 'normal' is considered to be about 1.5 per hour. The general consensus was to just watch him and to have a followup sleep study in 6 months. If the results are very poor (as in much worse than current), then early jaw surgery will be reconsidered. However, if the results are better or the same (or even marginally worse) the course of action could be varied: resume oxygen at night, CPAP, or possibly nothing at all. So again, we shall see...

Ethan also had a followup hearing test. This was actually his best test to date as he actually seemed interested and engaged and gave good results (as opposed to in the past where he seemed to get bored and then simply ignored the test after giving initially good responses). The results seemed to indicate he possibly does have some hearing loss in his right ear but over all, his hearing loss is not enough to be of any developmental hindrance. There will be yet another followup test in about 6 months or so when he will be about 3 years old and he will be old enough that they can administer a different type of hearing screen.

So overall the results were mixed. He is doing much better, but the results were not stellar. His sleep quality is still not considered 'normal' but it much, much improved. His speech is likewise greatly improved, but there is still work yet to be done. The common theme running through all the appointments today was, "see you in six months!".


- bob

Wednesday, June 22, 2011

Ethan's 6 Month Followup At Children's

Monday (6/20/11) was Ethan's 6 month (give or take) followup with Children's. He had another hearing screen followed up with visits from his plastic surgeon, social work, otolaryngology (ENT), and pulmonary (his sleep doctor).

His hearing screen was not great - but that was not due to the test results but rather a function of his age and their inability to get a good test in. Up until now, the tests consisted of him sitting in a sound proof room (on Dina's lap) while an assistant used toys and props to keep Ethan's attention focused on her/forward. Then, at random times, the tester (in the adjoining room) would play a sound. If Ethan looked in the direction of the sound, various things would light up and move. The sounds would be varied in amplitude, frequency (pitch), and direction. As long as Ethan looked in the direction of the sound, they would conclude he could hear that frequency.

The problem now is that Ethan is of the age where this kind of thing gets old very quickly and he eventually simply lost interest and would not look at anything except what was currently occupying his attention. He would look initially, but eventually, would stop looking, but at times would just mimic the sound himself instead of looking.

The test administrator herself remarked that he is of the age where the test may or may not work. Ostensibly, at his next hearing screen, the tests will be different as he will be at least 6 months older.

What results they did get were fairly good and consistent with previous results.

The visit with the plastic surgeon was uneventful. He examined the scar from the macrostomia repair and noted it was still fairly large. It is mostly on the inside of his mouth and therefore not that noticeable from he outside. He mentioned that if Ethan were to have an upcoming surgery, he might take the opportunity to go in and do a little to the scar to help soften it up (either by a very quick and minor procedure or a cortisone injection). This segues nicely into...

His visits from otolaryngology and pulmonary both indicate that Ethan will need to have his tonsils removed and at least some portion of his adenoids removed. This was no surprise given what has been going on these last few months. We hope to have this surgery scheduled by end of next week.

The plan is to continue the oxygen until the surgery, and then continue the oxygen for 1-2 weeks post surgery as he heals. Once he's recovered from the surgery, we will then take him off the oxygen until a follow up sleep study which will be 3 months later where he will be evaluated again. It is possible (though hoped not!) that he may need to go back on oxygen at that point.

In the worst case, should the tonsil and adenoid removal prove ineffective, they will put early jaw surgery back on the table as an alternative to help open up his airway. It is, however, expected that this upcoming procedure will alleviate all his current sleep problems.

- b

Monday, August 2, 2010

Hearing Test Redux

Ethan had his second scheduled hearing test to day at Children's. The results were very encouraging. Ethan, as of this point, has no fluid in his ears and demonstrated he is capable of hearing all the different speech sounds. The implication is that there is minimal to no risk of any speech development problems due to an inability to hear properly. Moreover, it appears that the ear tubes we thought were almost inevitable are, at least at this point, not needed.

By the nature of the test itself, they could not determine if one ear had any hearing loss or not. A more specific (and different type of) test would be needed to determine that. What this test *did* demonstrate is that Ethan has no hearing loss at all in at least one ear.

Yet more welcome and positive news!

- bob

Tuesday, April 27, 2010

Marathon Appointment Day

We were at Children's from 9 to 4 today. It's been a long time since we've had such a long day there. They combined the hearing screen, regular Cranial Facial visit, and pre op all into one visit.

The hearing screen indicated that Ethan has minimal hearing deficiency - but they attribute that to him still having fluid in his ears (both) due to his ear infection that he had a few weeks ago. They said it was not uncommon for fluid to remain in the ears even up to 6-8 weeks after the infection for infants and it can affect the results of the hearing screen. The doctor recommended another hearing screen in about 6 months. The hearing loss was not significant and due to the circumstances, the doctors were not concerned at all. The doctor also indicated that since hearing screens are $300 a pop - if you do too many of them, the insurance company will simply not pay for them anymore. So she recommends waiting 6 months for the next one rather than another at 2 months and another a few months after that.

The issue of PT tubes being inserted to help drain fluid from the ears was discussed. The doctor said that they will not even consider talking about that until Ethan has established a pattern of significant ear infections (like at least 3 in 12 months) and/or continually showing fluid in the ears (i.e. in 6 months - if he still has fluid in the ears, and then again 3-6 months again after that). It came up because it was indicated to us that children with CFM often have chronic problems with ear infections and fluid build up in the ears and the tubes help alleviate the issue. But in Ethan's case, it is way to early to tell and they will just watch and monitor him over the next 12 months.

Otherwise, the appointments were routine. Cranial Facial is very pleased with his progress and how he looks. They will want to see him next at post op. Pre op was uneventful. The doctor discussed the procedures with us. There will be a little scarring where the procedures will be done: one by each ear where the tags will be excised and one at the corner of the mouth where the macrostomia repair will take place. The doctor said that he would spend that night in the hospital and most likely go home the next day. Surgery is still on for June 3. Total time in surgery is slated to be about 2 hours.

One thing that the doctor mentioned is that for 2 weeks following the procedure, they will most likely want Ethan's arms to be be somewhat restrained so that he can't accidentally pull on/pull out the stitches. Since Ethan *really* likes to put things in his mouth, this will eliminate that ability. So it will be a very long and probably miserable 2 weeks for all of us. He will still be able to grab and play with toys - he just won't be able to put his hands to his mouth.

- bob

Tuesday, December 15, 2009

If Bad News Occurred In An Uninhabited Forest, Could It Get Worse?

If no news is good news, what I wouldn't give to have no news for a change.

So we got back from our visit at Children's with Ophthamology and ENT. The Reader's Digest version: Ethan has severe astigmatism in his right eye due to the presence of the dermoid. Starting from around 2-3 years of age, he will need glasses and patching to correct this and prevent the onset of amblyopia (a word you do *not* want to hear). The good news is that his eyes and vision are otherwise fine. His left eye is perfectly fine. The right eye, apart from the astigmatism is fine. The ophthamologist says that the dermoid is unlikely to change moving forward and whatever damage it was going to do: it's already done. His opinion is that while this is not good news by any stretch of the imagination, it is 'typical' for children such as Ethan suffering from Cranialfacial Microsomia: it is typical for children with CFM to have dermoids of this size, it is typical for dermoids of this size to cause astigmatism, and it is typical for the astigmatism to be of this severity.

There is no need to take any corrective action until about 2-3 years as his vision is still developing and that any difficiency in visual acuity from the astigmatism is outweighed (and will be until about 2-3 years of age) by the normal difficiency in visual accuity that is due to his age (i.e. his vision won't be developed enough until age 2-3 for the astigmatism to be noticed). As a side note: if no corrective action were to be taken at all, amblyopia wouldn't set in until probably around age 5 or so, so it is not of any immediate concern (hence no action until age 2-3).

Ophthamology also believes that in light of the above, the dermoid removal is purely optional and cosmetic (if we left it in, it wouldn't make the astigmatism worse or cause any other problems, and if we remove it, it won't make the astigmatism go away). However, if we wish to have it excised, he recommends postponing it until at *least* one year of age if not later as the surgery is extremely difficult before one year of age. Moreover, it is currently impossible to judge the depth of the dermoid and as such, impossible to know how it will look after surgery: they cannot *completely* excise it - what they do is shave off the top. So this leaves some of the dermoid behind which means that there will still be some opacity in the region of where the dermoid currently resides. How opaque it will be depends on how much is left behind which depends on how thick the dermoid is (which they won't know until pre-op which is at least 8 months away currently). Regardless, he did say it would "look much better".

ENT didn't reveal much. There is some inflamation of the tissues above the vocal chords. This may be due to reflux, it may be due to the presence of the NG tube, or it may be due to a combination of both. This result is pretty much congruent with what we expected after coming out of last week's visit and recommendation of the ph probe. I suppose the good news here is that they didn't see anything out of the ordinary or abnormal.

We discussed the possibility of having his frenulum clipped to allow for more tongue movement (this has been OTPT's recommendation all along) and they (ENT) recommend to do it while under general anesthesia during his upcoming macrostomia repair (they felt that there might be some bleeding and hence couple of stitches may be required and hence it wouldn't be something to be done in clinic). They also recommended moving his (more comprehensive) hearing test up from 8 months or so to within the next 1-2 months.

We are still awaiting scheduling of the ph probe. We hope to have word on this within the next 24-48 hours. With the holidays upcoming, we expect it won't be scheduled until January.

We also have an upcoming (regular) appointment with CranialFacial in January.

-bob

Tuesday, December 1, 2009

The Story So Far...

Gleaned from various status emails:
------------------------------------

8/28/09
It's been a long(!) two weeks but Ethan is home now. We gave Jonathan his presents from Ethan (a new Thomas train and a box of cookies). Jonathan loves his new train. Could care less about having Ethan home. :-) But at least we got a "Thank you, Ethan" out of him. Currently scheduled to be back at Children's on Sept. 21.

8/27/09
As of 8/27/09: We are still on track to come home today. The call on whether to come home today or tomorrow is entirely ours. The hospital is satsified with discharging him at any time now. If we feel we need an extra day to work with the feeding equipment and get familiar with it, we can stay. If we feel OK with it, we can leave. The equipment showed up yesterday. I used it yesterday and Dina used it last night. Not very hard at all (after you've used it once, it almost seems obvious how to use it). The opthamologist showed up yesterday to examine his epibulbar dermoid. While large, her opinion is that it is not currently interfering with his vision. She currently sees no indication to think his vision is impaired in any way. It will, however, need to be continually monitored and, ultimately, most likely will have to be removed. They ran the hearing test again today. They have to run the test when the baby is sleeping and not moving. Ethan apparently was very restless in his sleep resulting in them having to run the test 3 times (movement can give false positives). He passed 2 out of 3 times. I personally view this with some suspicion and will hold judgment until his hearing is evaluated at Children's. But it does give some hope that he may not actually require surgery in his middle ear. We contacted Children's and they are supposed to get back to us today regarding his next appointment. I hope this will be within the next 1-2 weeks. His feeding is showing improvement but it is painfully slow. But progress is progress. The goal is to get him off the feeding tube entirely within 1-2 months. Ethan failed his car seat test. This means we need to buy a new car seat even though we already have one (he's too small for it currently). We will buy a new one and use it for all of 1-2 months and put him in the old one (that fits in the stoller) when he's bigger.

8/22/09
We got back to the hospital from Children's about 4:30PM. Several specialists examined him. It is now officially Cranialfacial Microsomia as the diagnosis. The doctor doesn't like the other names (Goldenhar's Syndrome, Hemifacial) - but that's his personal preference. The diagnosis is the same which is what we first diagnosed. Nothing will be done to Ethan surgically until he is about 1 year old. At that point, they will probably address the lateral cleft in his mouth, and the ear tags (at our request - the ear tags are purely cosmetic and Children's leaves that entirely up to the family). The reason for the wait has to do with the proxmity of these areas to the facial nerve. Ethan's jaw is actually far worse than I thought. His entire lower left jaw is underdeveloped/malformed. On his left side (good side), the Ramus is smaller than it should be (the bone that extends from the base of the Mandible to the upper jaw where it hinges together). His right Ramus is almost non-existant. Moreover, the base of the mandible on the right side is shorter. This can and will be addressed surgically, but not until he is about 2-3 years of age. It is almost certain he will be deficient in hearing on his right side. To what extent is not currently known, but like the article you sent me, it won't be addressed until he is at least 4 years of age. The epibulbar dermoid on his right eye the doctor felt will probably need to be removed due to it's size. This again will not take place until he is at least 1 year old. His spine cannot be properly evaluated until around one year of age. The plan going forward is once we get discharged from the hospital, we will setup another appointment with Children's in the following 1-2 weeks (depending on when we can get an appointment). At that time, they will concentrate on working with us to get him feeding better. The other disciplines will also come to examine him as a sort of "heads up" as for what will be coming their way in the next year. After that appointment, they will tell us when is the next time we should come in. They will monitor him over the next few months. If anything changes, the surgical schedule may be brought in (i.e. the epibulbar dermoid is growing faster than they would like/anticipate - so it will be removed sooner than after 1 year, etc). But if nothing changes for the worse, we are probably on track for having the first procedure done around 1 year from now. The doctors at Children's felt that Ethan can be discharged now and sent home with the feeding tube. We will work with Children's to work on his feeding to get him off the tube. This will be a long and time consuming process. They have shown us methods to tape that side of his mouth shut (basically closing off the mouth where it normally should be closed) and it seemed to help with the feedings but he is still having difficulty. The hospital has begun the process of discharge. With luck, he will be home within a week. They need to setup an initial plan for us going forward for working on his feeding, ordering the equipment for us (for the feeding tube) or point us to a vendor, clearing everything through insurance, etc. So in a nutshell: Ethan will be home in a week (give or take). He will still be on a feeding tube but will will be working with Children's to get him off that. This will take some time. We will have "regular" appointments with Children's for monitoring and evaluation. He will require at minimum of 7 surgeries (3 for the jaw - minimum, 1 for the mouth, 1 for the ears, 1 for the ear tags, and 1 for the eye). Surgeries will begin at around 1 year of age and continue until probably around 4-5 years of age. The studies on this indicate that it is genetic. They do not understand the genetics. Ours is a typical case - no history of it on either side and then it appears sporatically. Therefore, they think the genetics behind it are quite complicated - some specific set of genes on one side with specific set of genes on the other side coming together in a sort of "perfect storm". Therefore, currently, they believe the odds of siblings having children with CFM are very low - i.e. because it appeared in our family now, the odds are still low that Elaine, Andy, or Ryan will have this problem.

8/19/09
The on call NICU physician said he had indeed seen this before (this was a different doctor). His diagnosis is specifically Goldenhar's Syndrome - which is basically what we suspected: it's a type of Hemifacial Microsomia. He is sure of it. From his examinations, it seems that Ethan is very healthy and that most of the manifestations of the syndrome are cosmetic. Ethan had his hearing test done. The left ear passed. The right ear did not. So they will retest again tomorrow. If the results are the same, we will go to Children's to have a much more comprehensive hearing test done. If he fails the test tomorrow, it does not necessarily mean he does not have hearing in the right ear. It means we need a more comprehensive test. He thinks the dermoids in his right eye should not impair his vision. They may lead to astigmatism later on in life but he said the team at Children's will evaluate and decide if they need to be removed. If they do not impair sight and will not cause any future problems, then the only issue is one of cosmetics and we can have them optionally removed at a later date. His recommendation was to start the process of meeting with Children's immediately as it is in fact a "process" you go through - you don't just call for an appointment. We start the process now because it may be months before we actually get into to Children's to meet with their team. However, he did say that if through some miracle they had an opening and could see us before Ethan is even discharged, the hospital will find a way to make sure we do not miss the open slot at Children's - even if that means they need to send a nurse with us to Children's. In other words, the hospital will do what it can to help us through the process and will in no way be a hinderance to us if Children's is ready before Ethan is. Dina has already made the initial call to Children's and we are waiting to hear back from them. Ethan is not making huge progress in eating. He is hungry more often and they are feeding him increasingly larger amounts and he is keeping it all down. The issue is that he still is not very capable of feeding himself (either by breast or bottle). However, when I did go to visit this afternoon, he sucked down 42 ml orally leaving only 8 ml for the feeding tube. But it seems he's not always consistent.


8/17/09
So as of 8/17/09, this is where we are: Ethan was born with Hemifacial Microsomia. It is sometimes referred to as Goldenhar Syndrome or Cranialfacial Microsomia (among the dozen names this condition has). There is no official diagnosis yet as only the staff at Children's is qualified to make this diagnosis. I spent countless hours researching his irregular physiology until I came to this conclusion. The hospital staff seems to concur with my conclusion - but again - only Children's can confirm my/our suspicions. He has trouble feeding and consequently is in NICU where they are working to get him to feed regularly/properly. Some progress has been made but he will not be discharged from the hospital/NICU until he can consistently breastfeed/bottlefeed 30ml per session. He is not able to do this so they are supplementing his breast/bottle feedings with a feeding tube. The reason is that he tires easily and usually falls asleep before he can ingest that amount orally. This *may* be due to the fact that he was 2 weeks early. This probably has nothing to do with his HFM (though it *may* contribute as he may have to work harder to feed than normal because of his mouth). Once he is discharged and can come home, we will be then set up to meet with the cranialfacial team at Children's for a proper clinical diagnosis and then a course of (surgical) treatment. The good news (it's increasingly hard to come by recently) is that Children's specializes in this and are extremely familiar with this. Assuming this is indeed what it is (and I have never been more sure of anything in my life). Ethan is otherwise very healthy. Cranial and renal ultrasounds revealed nothing nor did the echo cardiogram and the abdominal x-rays. Hearing tests have not yet been run but anecdotal behavior suggests his hearing is OK (that is our opinion - nothing official). He is not in any discomfort, all his internal organs are all functioning, and he is behaving fine. Dina was discharged from the hospital on Sunday. She is staying at the hospital in Ethan's room so she can provide regular (every 3 hours) breastfeedings. I am now at home with Jonathan. My folks have left (will return after Labour Day - they could not stay longer as they need to take specific medications and did not bring enough to prolong their stay). Dina's mom will be helping me at home so I can resume working from home (or back on site if required/requested).

8/14/09
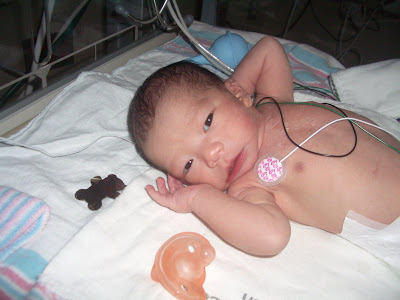
So to keep you updated or to inform you if I inadvertantly did not initially inform you (apologies if so): Dina gave birth by c-section this morning at 12:39AM. Dina's doing really well (especially compared to last time). Ethan (currently his name - may change again!) was born 5 lbs 8 oz. I forgot his length. He does have a few issues and is currently in NICU. He was taken to NICU after birth, spent the night with us in Dina's room, but after the AM pediatric assessment, was sent back to the NICU. He's had some tests and the current status from the doctor is that he has not heard anything and that no news is good news (i.e. if something were wrong, they would have informed him immediately). Dina is slated to be discharged Sunday (tentative). No ETA on Ethan being discharged from NICU. One issue is that he is not eating and is currently being tube fed. Even if there are no other issues, they will not let him out until he is eating.
-bob